What happens before the beeps?
A useful appointment begins with the situation that brought you in. The clinician may ask when the change started, whether it affects one or both ears, what listening situations are hardest, and whether you have pain, drainage, dizziness, tinnitus, sudden change or recent noise exposure. Those details influence both the test plan and the urgency of a medical referral.
Otoscopy is the visual inspection of the ear canal and eardrum. It can reveal an obstruction or another reason a test may need to be delayed or interpreted cautiously. It does not measure hearing by itself.
Middle-ear testing
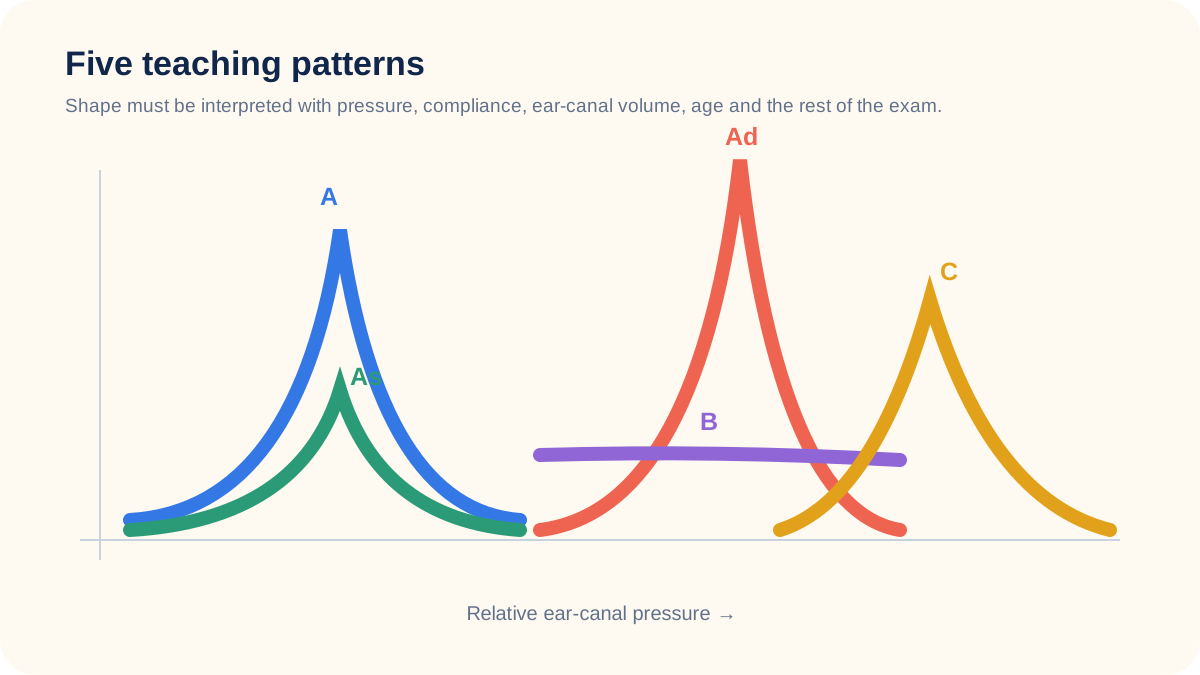
Tympanometry changes air pressure in the ear canal while measuring how the eardrum and middle-ear system respond. Acoustic reflex measures can add information about a reflex pathway involving the middle ear, inner ear, auditory nerve and brainstem. A curve is a clue, not a diagnosis: the same broad shape can have more than one explanation, and ear-canal volume and the rest of the examination matter.
If your report contains Type A, As, Ad, B or C, use our tympanogram guide to understand the vocabulary before discussing your own result with the testing professional.
Pure-tone and bone-conduction testing
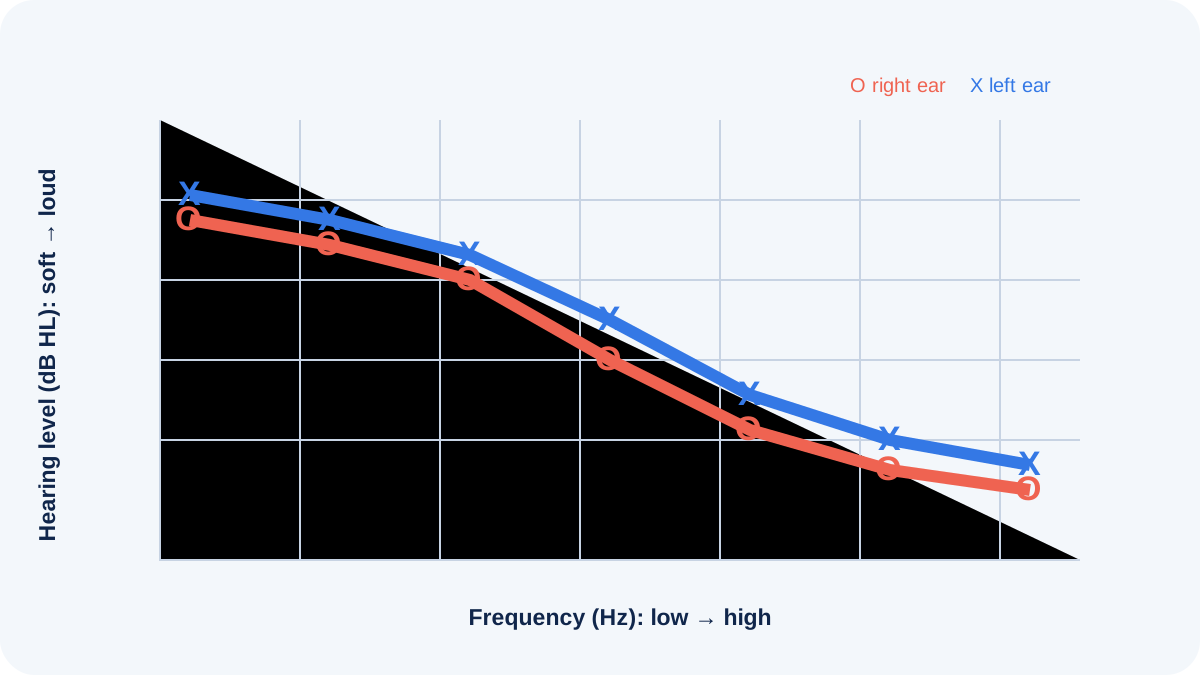
Pure-tone testing estimates the softest tones you respond to at several frequencies. Air-conduction testing follows the usual path through the outer, middle and inner ear. Bone-conduction testing sends vibration through the skull toward the inner ear. Comparing the two helps the clinician describe a conductive, sensorineural or mixed pattern.
The plotted thresholds form an audiogram. A pure-tone average can summarize selected frequencies, but an average can hide a steep high-frequency loss or an important difference between ears. The configuration and your real-world communication needs are often more useful than one number.
Speech measures and the real-world gap
Speech reception or speech recognition threshold testing asks how softly familiar speech can be identified. Word-recognition testing asks how accurately a list can be repeated at a level chosen by the clinician. Performance in a quiet booth does not reproduce a restaurant, team meeting or moving vehicle. If your main problem is speech in noise, say so and ask how the test battery addresses that complaint.
A worked example
Consider an adult who hears low-pitched tones near the normal range but needs much louder high-pitched tones. A single average may look only mildly reduced, while consonants, children’s voices and speech in noise remain difficult. The useful next step is not to label the person from the average alone; it is to connect the frequency pattern, speech results, ear-specific differences and daily situations.
Questions to take to the appointment
- Is the change conductive, sensorineural, mixed or still uncertain?
- Are the results symmetrical between ears?
- Do any findings call for an ENT or other medical referral?
- How do speech scores compare with pure-tone results?
- Which two listening situations should we use to judge whether an intervention helps?
Seek prompt medical care for a sudden hearing change, severe ear pain, drainage, new marked dizziness, or another urgent symptom. This guide cannot determine the cause of an individual result.
Build an evidence record
Read the history, otoscopy, middle-ear results, air and bone thresholds and speech findings as one evidence set. Agreement strengthens an interpretation; disagreement is a reason to check method, masking, ear status or an additional measure rather than select the most convenient number.
Write the date, ear or listening condition, equipment or service involved and the decision the evidence is meant to support. Preserve the original report or agreement rather than a cropped screenshot. When two results disagree, record the mismatch and ask what additional check would resolve it. Reliable decisions make uncertainty visible instead of silently converting it into certainty.
Worked decision
An adult reports difficulty in meetings. Pure-tone thresholds show a high-frequency reduction, quiet speech remains relatively strong and tympanometry is broadly typical. The plan tests verified amplification and a distance solution instead of treating the middle ear or dismissing the complaint.
This example shows why the same label can lead to different actions. The recommended next step follows the measured barrier, urgency and complete context. It does not assume that a more expensive device, a louder setting or a single test result is automatically more useful.
Prepare and verify the next step
Request the complete report, the legend, ear-specific results and a plain-language summary of what remains uncertain. Define two daily tasks for follow-up and ask which symptom or measured change would trigger medical referral.
Choose a repeatable task and define success before the change. Record distance, noise, speaker, program, comfort, handling and any failure. Repeat the task after adjustment and keep a backup communication route while evidence is incomplete or equipment is unavailable.
At follow-up, compare the result with the original goal rather than asking only whether the person “likes it.” Confirm what improved, what remained difficult, whether setup was independent and whether the solution worked for other speakers or rooms. Document maintenance, repair and retesting responsibilities so a successful trial can become dependable daily access.
Share only the information needed for the decision. A clinician may need symptoms and test history, while an employer may need the functional barrier and proposed access method rather than a complete medical record. Clear boundaries protect privacy and keep the discussion focused on the task.
Important boundary
A complete evaluation can describe type, degree, configuration and functional evidence, but it may not identify a single cause.
Seek prompt professional care for sudden hearing change, severe pain, drainage, acute dizziness, neurologic symptoms or a retained object. Product features, policies and official guidance can change; verify current instructions and primary sources when the decision affects health, safety, money or legal rights.
Sources and review notes
Sources were checked for this editorial update on September 26, 2026. External guidance can change; follow the linked source for the current version.
- NIDCD — Do You Need a Hearing Test?
- American Speech-Language-Hearing Association — Hearing Testing
- Legacy technical module and contributor record
This page provides education, not an individual diagnosis, treatment plan, legal opinion or billing decision. Historical expert contribution is credited only where supported by the original project record; it does not imply review of this update.